

In the videos for this weekend, I will start by deconstructing the absurd nonsense floating under the title of “nociplastic pain”, which I began to discuss yesterday.
You can take it or leave it, but I will advance the argument that this nonsensical categorization is just a garbage pail to receive "medically untreatable conditions" that now have a new treatment option based on this absurd categorization of “nociplastic pain” which “justifies” the use of an entire category of dangerous, expensive and therapeutically worthless drugs.

Part1: My initial review and critique
The first video that will be made available is completely raw and uncut and will later be at least partially edited if not only to improve certain aesthetics or sound quality, etc.
The first unedited video will be made available for free: so take advantage of it while you can because later after I've invested time to edit the video only a certain portion will remain available for free and the remainder will be available for people who actually pay to support this work.
The edited version is now available with substantiation of my assertion
Part2: “Nociplastic pain” is simply a garbage pail to receive very treatable conditions that the medical profession refuses to treat effectively
Confirming the opinion that most medical doctors are incapable of independent thought, this new categorization of pain has received a list of very treatable and explainable conditions that the medical profession as a hole has repeatedly proven itself incapable of understanding, despite the fact that some of us have understood and have explained these conditions for more than two decades.
I do not believe that any rational intelligent literate person can look at this new categorization of “Nociplastic pain” and considerate valid. You are welcome to disagree with me and you are also welcome to think that the Earth is flat and that President Nixon used a land telephone to talk to astronauts on the moon in 1969.
The medical profession is putting all of its greatest failures into one single category, despite lacking any biological rationale, let alone therapeutic success:
restless leg syndrome,
chronic fatigue syndrome,
fibromyalgia,
temporomandibular disorder,
migraine or tension headache,
irritable bowel syndrome,
multiple chemical sensitivities,
whiplash injury
Any semiconscious clinician will note the stupidity of putting these divergent conditions into the same category, and any expert-level clinician should feel nauseous or at least offended by this absurdity.
Part3: My biochemically-plausible clinically-justified evidence-supported correction to their miscarriage of medical science
What they present as a mystery I can solve spontaneously and I will do so in the second video so be subscribed and stay tuned.
As a general rule, the more names a condition has (especially when it is called a “syndrome”) and/or the more weird and nonsensical the name is for a condition, the more likely is the hijacking of that condition for medical-pharmaceutical profiteering:
Example: Type-2 diabetes was formerly called “glucose intolerance” to underscore the fact that these patients had lost the ability to tolerate overconsumption of carbohydrates and therefore the obvious solution was to avoid carbohydrates to restore physiologic function. But a diet-centered approach did not maximize drug profiteering, so the condition was renamed “syndrome X” (eg, Syndrome X: is it for real? Genet Epidemiol 1998) in the 1990s and then renamed to “insulin resistance” to complicate the understanding and then sell more drugs, especially pancreas-pushing Sulfonylureas—given as pills to force the beta-cells in the pancreas to produce and release more insulin. Later, “bariatric surgery” was pushed as the definitive treatment, but only after many years of drug pushing to maximize profits from both.
Example: Complex regional pain syndrome (CRPS) was previously called “reflex sympathetic dystrophy” (RSD) because RSD describes the neurological pathways involved and the physical appearance of the consequences. CRPS does not tell anyone anything except that it is something painful and that it is “complex” which is the entire goal of the nomenclature—make doctors think the condition is too complex to understand so they will be intimidated and passive so that they just quit thinking, quit searching, and just use the drug buffet guidelines to keep these patients on drugs for the rest of their lives, which is obviously the most profitable.
After decades of therapeutic failure in the management of chronic pain, the medical-pharma profession stopped looking for new solutions and new causes, and instead they just created a new category of pain called “nociplastic pain” which is defined as “your pain is causing itself and you’ll have to be on maximum drugging and multiple drugs for the rest of your life.
This renaming was a rebranding in 2017 just in time for the 2018 launch of the new migraine drugs that cost $7,000 - $10,000 per year with a failure rate of about 6 per 7 patients (85%!!). Now doctors were authorized to keep a straight face when they lied to patients and just told them that “your pain is causing itself and you’ll have to be on drugs for the rest of your life.”
This rebranding of pain was given 3 different names:
Disorder of sensory processing = your brain is screwed up
Neurogenic neuroinflammation = your brain is causing its own inflammation
Nociplastic pain = we are desperate for a confusing name so now we are going to say that your pain is reforming your brain and it is your brain’s fault!
Example of “Disorder of sensory processing” = your brain is screwed up
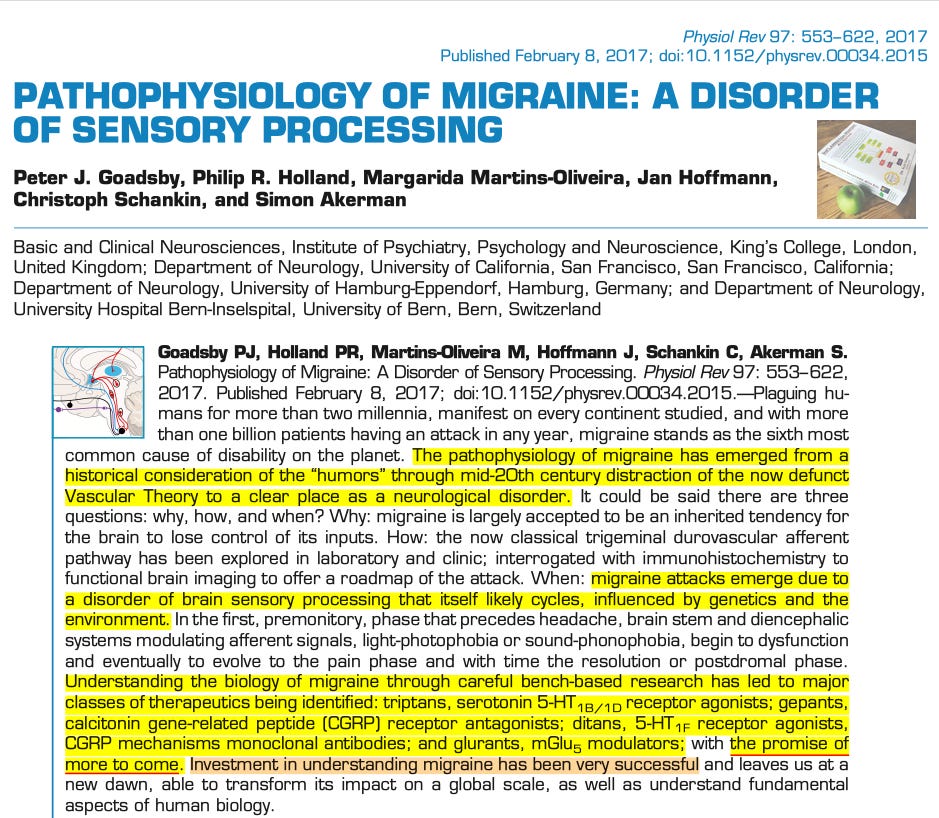
Example of Neurogenic neuroinflammation = your brain is causing its own inflammation

Example of Nociplastic pain = we are desperate for a confusing name so now we are going to say that your pain is reforming your brain and it is your brain’s fault!

I have been clear and consistent for years per my books, articles and videos (linked below) that I think the medical management of these chronic pain conditions is an INTENTIONAL FAILURE and example of STRATEGIC STUPIDITY in order to sell more drugs and maintain control over these populations of patients.
Furthermore and clearly from a Nietzschean perspective, this is what he called SEDUCTION BY GRAMMATICAL CONSTRUCTION which is using language to confuse people and thereby control them.
SEDUCTION BY GRAMMATICAL CONSTRUCTION is using language to confuse people and thereby control them.
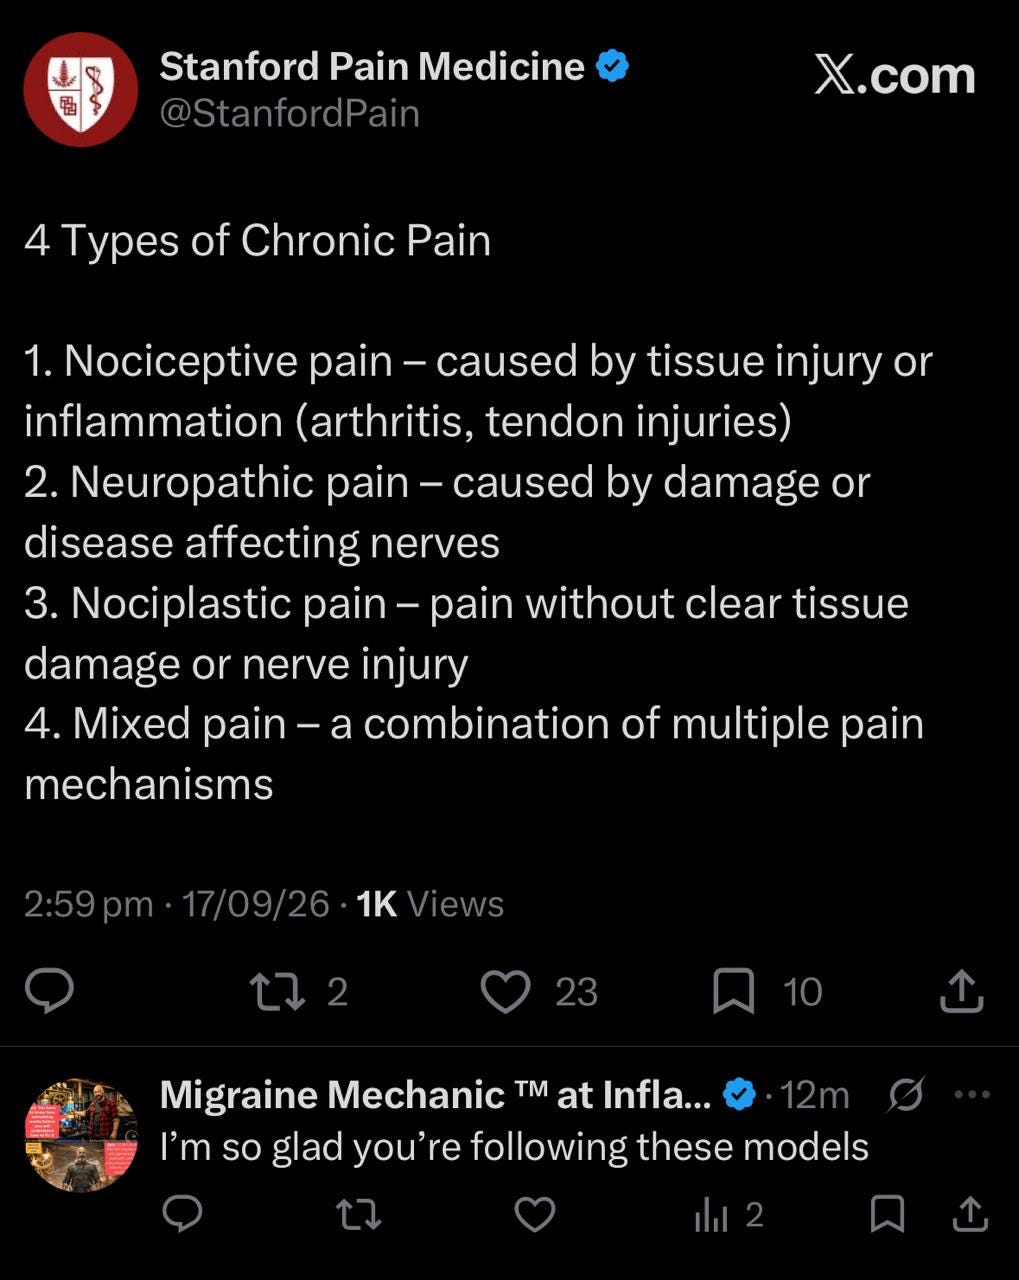
Thanks, STANFORD PAIN MEDICINE! I feel so happy when they keep proving that I’m right about their misperception and mismanagement of CHRONIC PAIN: My new work on MIGRAINE is going to Flip the Script!
Stanford Medical School/Center just published a recent post under the title of “Stanford Pain Medicine“ describing “four types of chronic pain” as you can see in the image provided below, which includes my comment to them.
As you can imagine, I’m quite delighted that they still think this way because this proves that I was right when I said six years ago that the entire medical profession is hopelessly lost in their perception of chronic pain conditions and that’s why their treatments for chronic pain have a 97% failure rate, even by their own pro-medical guideline-endorsed standards.
If the medical model of “chronic pain” is wrong, then “targeted treatments” are only going to hit the wrong targets, and this explains the >95% failure rate of medical pain guidelines.—DrV
They keep falling into the same hole of bad modeling, logical errors, bad treatments and 30 years of therapeutic stagation, bad failure-guaranteeing guidelines, and perpetual nutritional ignorance.
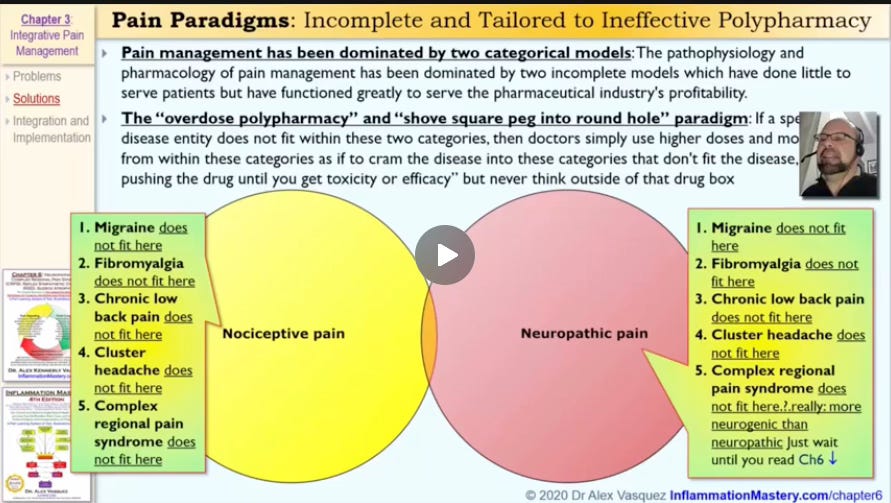
You can see in the screenshot below from my video review of “vitamin D deficiency in chronic pain” that I was already critiquing this outdated medical model 6 years ago, even when I myself still had CRPS (!!!) as I discussed recently.
You will have noticed in my video review of “the role of vitamin D deficiency in chronic pain” that I specifically attacked the medical model of chronic pain because of its emphasis on these two types of chronic pain—nociceptive and neuropathic—that they most commonly treat with their ineffective drugs. If the model is wrong, then “targeted treatments” are only going to hit the wrong targets.
They feel very proud of themselves that they have now added a third condition which is called “nociplastic pain“ which is an extension of the absurd “neurogenic neuroinflammation” model published around 2016 which I addressed in my correspondence to the journal Nature Reviews Rheumatology after deciphering their physiology gaslighting titled—citations for those publications are provided here:
Littlejohn G. Neurogenic neuroinflammation in fibromyalgia and complex regional pain syndrome. Nat Rev Rheumatol. 2015 Nov;11(11):639-48
Vasquez A. Neuroinflammation in fibromyalgia and CRPS is multifactorial. Nat Rev Rheumatol. 2016 Apr;12(4):242

HUMAN MICROBIOME AND DYSBIOSIS IN CLINICAL DISEASE are being re-uploaded in Feb-Mar 2025 to provide direct and reliable access through the substack platform:
Can you answer these 10 questions on dysbiosis and microbiome?
VIDEO with discussion of QUESTIONS and ANSWERS 1-5 with Test-Taking Strategies
QUESTIONS and ANSWERS for Dysbiosis & Microbiome (6-10) with Test-Taking Strategies
Microbiome Dysbiosis (1) Course Overview and Introduction to Major Concepts and Mechanisms


