

You can find plenty of conversation about the connection between chronic pain conditions and disorders of Kynurenine metabolism, but the question remains: what are you going to do about it?
Are you going to test for it?
Are you going to treat for it?
Are you going to ignore the whole topic—because you don’t know about it?
Are you going to ignore the whole topic—because you already know intuitively what to do about it?
Another complicating issue about KYN metabolism is that it is filled with paradox from a clinical standpoint because various components can be harmful, proinflammatory, anti-inflammatory, neurotoxic, neuroprotective. But the other clinical perspective is one of importance, clarity, and priority: how much time and effort are we going to give to this pathway at the expense of other more actionable and solid clinical priorities?
The last time that I reviewed KYNURENINES was in the MICROBIOME-DYSBIOSIS PROGRAM in the videos on the GUT-BRAIN AXIS—see the links provided below!
Examples of the laboratory testing:
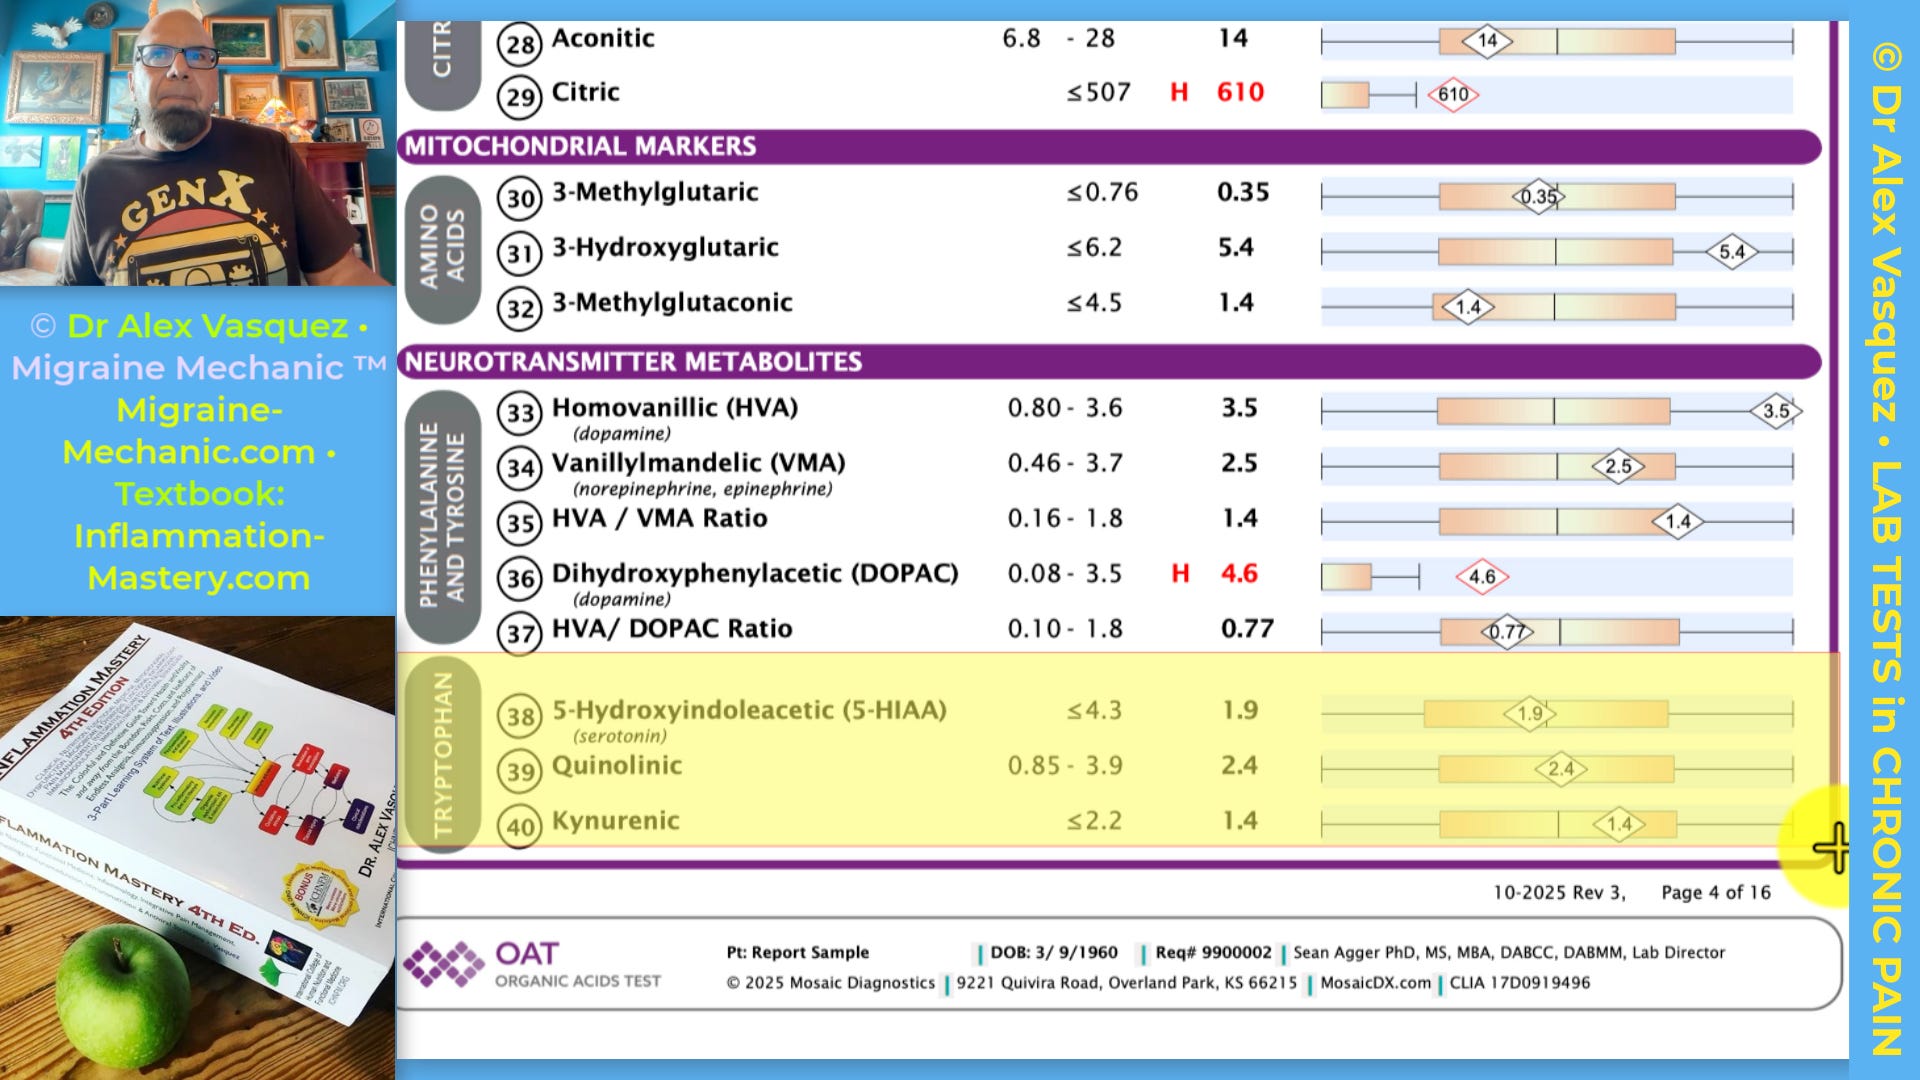
The video discussion on Kynurenine testing as related to chronic pain (imaged above) has been recorded and will be posted soon— while the video is being edited and processed, you have time to review previous conversations related to this topic.
“Another complicating issue about KYN metabolism is that it is filled with paradox from a clinical standpoint because various components can be harmful, proinflammatory, anti-inflammatory, neurotoxic, neuroprotective. But the other clinical perspective is one of importance, clarity, and priority: how much time and effort are we going to give to this pathway at the expense of other more actionable and solid clinical priorities?” DrV
Examples of the conversation in research:


The video discussion on Kynurenine testing as related to chronic pain (imaged above) has been recorded and will be posted soon— while the video is being edited and processed, you have time to review previous conversations related to this topic. The last time that I reviewed KYNURENINES was in the MICROBIOME-DYSBIOSIS PROGRAM in the videos on the GUT-BRAIN AXIS:
Can you answer these 10 questions on dysbiosis and microbiome?
VIDEO with discussion of QUESTIONS and ANSWERS 1-5 with Test-Taking Strategies
QUESTIONS and ANSWERS for Dysbiosis & Microbiome (6-10) with Test-Taking Strategies
Microbiome Dysbiosis (1) Course Overview and Introduction to Major Concepts and Mechanisms
Microbiome Dysbiosis (2) Physiologic and Pathologic Mechanisms of Dysbiosis and Subclinical Microbial Colonizations (VIDEO:1hour,15minutes)
Microbiome Dysbiosis (3) Prototypes of Dysbiosis-Induced Disease(VIDEO:1hour,42minutes=102minutes)
Microbiome Dysbiosis (4) Conceptual Expansion Exploring Clinical Testing, Microbial Relevance and Irrelevance [VIDEO:1hour,18minutes=78minutes]
Microbiome Dysbiosis (5) Microbial Consequences in the Mouth, Oral Cavity[VIDEO:1hour,44minutes=104minutes]
Microbiome Dysbiosis (6) Microbial Imbalances in the Respiratory Tract and Sinuses [VIDEO:1hour,35minutes=95minutes]
Microbiome Dysbiosis (7) Dysbiosis by Location—Genitourinary Tract
Microbiome Dysbiosis (8) Dysbiosis by Location—Blood, Tissue, Parenchymal Dysbioses
Microbiome Dysbiosis (9) Dysbiosis by Location—Skin and Environmental Dysbiosis
previous posts in this series are provided below
LABORATORY TESTING in CHRONIC PAIN (8) and the Progress of the New Protocol including Applied Molecular Biology
PDF article provided below, as cited in the video—
you know it is a good article if it talks about me and says nice things :-)


Today’s video:
This series will focus on ANALYSIS AND ACTION
What tests in what context
What are you going to do about it
Any social or “big picture” considerations
My history with this material:
Yes, we actually had dedicated classes in Clinical Laboratory and Patient Management in chiro/ND school while none of this was mentioned in “medical school”—just like Radiographs, Clinical Therapeutics, EENT, and a bunch of other important topics that needed dedicated courses.
Decades of reviewing lab tests in patient care.
Most common and important lab tests are reviewed in Chapter 1 of Inflammation Mastery 4th Edition.
Click here to see the first few pages, including the table of contents and index (size: 6 MB)
Click here for a larger sample with photos (size: 43 MB)
I have taught many courses that include laboratory interpretation including Orthopedics, Rheumatology, and Clinical Laboratory Medicine—the latter for about 4 or 5 years in a Master’s / Postgraduate program for doctors, and by the final year (2011) the class was actually competent—those course notes are now included in Inflammation Mastery 4th Edition.
I taught theLaboratory Assessment lecture of our 3-instructor Immune/Inflammatory Disorders Conference at the Institute for Functional Medicine (where I was Faculty since 2003) until 2013 until IFM President David Jones “Mr Spirituality and Community” sent me a hyperarrogant email demanding free access to my 2013 International Conference on Human Nutrition and Functional Medicine, which I of course rejected out of respect for my own work (I paid for the entire conference myself, including venue, printed notes, travel, hotel, food, and generous compensation for the presenters) and also respect for my graduate students, some of whom were single mothers working up to 2 jobs to pay for their tuition; later that year, IFM announced my replacement on Facebook but never had the courage to tell me directly. So much for my 11 years of nonprofit “service” and helping grow the organization from a time when they could not even pay their faculty!

Clinical-Laboratory Assessment of Chronic Pain:
You have to know the “core competencies”—the more you know, the better.
You have to have systems and strategies for patient assessment, this demonstrates that you know what to look for (eg, what is likely, and what is dangerous) and that you have thought out the process ahead of time
You have to look for and try to make more than one diagnosis at a time; then each diagnosis carries its responsibilities. Just because you find a diagnosis does not mean that you found the only diagnosis— “Patients are entitled to more than one disease.” Ron LeFebvre DC
Real experts know and respect real diseases, and they rule-out real diseases before looking for “functional” problems
You must have backup plans for your strategy because sometimes your first strategy does not work perfectly.
What if your patient refuses lab tests?
What is the difference between CHRONIC PAIN with a ferritin of 4 vs a ferritin of 450, assuming a benign CRP et al?
Most common and important lab tests are reviewed in Chapter 1 ofInflammation Mastery 4th Edition.


LABS for CHRONIC PAIN (5) What is the probable diagnosis and next lab test?

Image and case presentation from PMC1114910 with full-text PDF provided below:


Can you answer these 10 questions on dysbiosis and microbiome?
VIDEO with discussion of QUESTIONS and ANSWERS 1-5 with Test-Taking Strategies
QUESTIONS and ANSWERS for Dysbiosis & Microbiome (6-10) with Test-Taking Strategies
Microbiome Dysbiosis (1) Course Overview and Introduction to Major Concepts and Mechanisms
PDF article provided below as cited in the video—you know it is a good article if it talks about me and says nice things :-)


